

Quick take: Choosing between a midwife and an OB/GYN for your first pregnancy depends on your comfort level, medical needs, and birth philosophy. Midwives offer more personalized, holistic care and are more likely to support natural birth, while OB/GYNs provide immediate access to advanced medical interventions. Both are safe options for low-risk pregnancies, but your unique circumstances—like medical history or insurance coverage—will guide the right choice. Start by asking yourself: Do I want a team that prioritizes natural birth, or one that’s ready for any medical scenario?Midwife vs. OB/GYN for Your First Pregnancy: What’s Right for You? --- ### **The 3 AM Realization That Changed Everything** It was 2:47 AM, and your hands were shaking as you scrolled through birth stories online. One mom swore by her midwife’s hands-on approach, another gushed about her OB/GYN’s reassuring presence in the delivery room. You’re three months pregnant, and suddenly, the decision feels like a high-stakes puzzle. *Do I want a birth experience that’s guided by nature’s rhythm or one that’s backed by the latest medical technology?* The truth is, there’s no one-size-fits-all answer—but there *is* a way to make the choice feel less overwhelming. This guide is here to help you cut through the noise, understand the key differences, and trust your instincts as you navigate this exciting (and sometimes anxiety-inducing) first pregnancy. --- ### **How to Decide: Midwife vs. OB/GYN for Your First Pregnancy** The first step isn’t comparing qualifications—it’s asking yourself: *What matters most to me?* Do you envision a birth where you’re encouraged to move freely, using gravity and position changes? Or do you want a plan B ready if things take an unexpected turn? Your answer will shape whether you lean toward a **certified nurse-midwife (CNM)** or an **OB/GYN**. Here’s how to start thinking about it: - **Natural birth support vs. medical readiness**: Midwives are trained to help you navigate labor naturally, while OB/GYNs are prepared for interventions like C-sections or forceps deliveries. - **Continuity of care**: Midwives often see you for all prenatal visits, labor, and postpartum care, fostering a deeper relationship. OB/GYNs may rotate staff, though you’ll always have a primary provider. - **Medical history**: If you have high-risk factors (like gestational diabetes or hypertension), an OB/GYN might be the safer choice. For low-risk pregnancies, midwives offer a more holistic approach. - **Insurance and cost**: Both are typically covered, but midwife care can sometimes be more affordable or require out-of-pocket payments for home births. Always check your plan’s details—[here’s how to navigate insurance for pregnancy care](link-to-insurance-guide-if-available). *Many women tell us they felt overwhelmed by the choice until they realized it wasn’t about “better” or “worse”—it was about aligning with their values.* One reader, Sarah, described her experience: *“I thought midwives were only for hippies, but my friend had a beautiful, low-intervention birth with hers. I realized I wanted someone who’d listen to me, not just follow a protocol.”* Your pregnancy is a journey, not a checklist—so let your instincts guide you. --- ### **Midwife vs. OB/GYN: Qualifications and Training Breakdown** Before diving into care styles, it’s helpful to understand what each professional brings to the table. Both are highly trained, but their backgrounds and approaches differ. | **Aspect** | **Certified Nurse-Midwife (CNM)** | **OB/GYN (Obstetrician-Gynecologist)** | |--------------------------|------------------------------------------------------------|-----------------------------------------------------------| | **Education** | RN + master’s or doctoral degree in midwifery | Medical degree (MD or DO) + residency in OB/GYN | | **Licensing** | Licensed by state boards; certified by the American Midwifery Certification Board (AMCB) | Board-certified by the American Board of Obstetrics and Gynecology (ABOG) | | **Focus** | Holistic, patient-centered care; emphasizes natural birth | Medical management; prepared for high-risk scenarios | | **Where They Practice** | Hospitals, birth centers, homes | Hospitals (often with private practices) | | **Typical Patient Mix** | Low-risk pregnancies, first-time moms, women seeking natural birth | All pregnancies, including high-risk or complex cases | *Fun fact: Midwives have been guiding pregnancies for centuries, and their modern training includes advanced skills like emergency obstetric care. OB/GYNs, meanwhile, undergo extensive surgical training, making them the go-to for complex deliveries.* **Key takeaway**: You don’t have to choose based on credentials alone. Instead, ask: *Does their training align with the kind of birth experience I want?* --- ### **What’s the Average Number of Prenatal Visits with a Midwife vs. OB/GYN?** One of the first practical differences you’ll notice is the frequency of prenatal visits. Both care models follow guidelines from the **American College of Obstetricians and Gynecologists (ACOG)** and the **World Health Organization (WHO)**, but the *style* of visits can vary. - **Midwife care**: - Typically **12–16 visits** over the course of pregnancy (more frequent in the first and third trimesters). - Visits often last **45–60 minutes**, allowing time for holistic discussions (nutrition, emotional well-being, birth planning). - Home visits may be offered, especially in the third trimester, for a more personal touch. - **OB/GYN care**: - Usually **10–14 visits**, with some providers offering **telehealth check-ins** to reduce in-person visits. - Visits are often **shorter (20–30 minutes)**, focusing on medical monitoring (blood pressure, weight, ultrasounds). - More likely to include **specialist referrals** (endocrinologist for gestational diabetes, cardiologist for heart conditions) if needed. *Pro tip: If you’re juggling work or other commitments, ask your provider about virtual visits. Many OB/GYNs now offer ultrasound reviews via video, which can save you a trip to the clinic.* ---
 ---
### **How Do Midwives Handle Emergencies vs. OB/GYNs During First-Time Labor?**
This is where many women’s concerns peak. *What if something goes wrong?* The good news: **both midwives and OB/GYNs are trained to handle emergencies**, but their protocols differ.
#### **Midwife Emergency Response**
- **Primary setting**: Hospitals or birth centers (home births are rare for first-time moms due to higher risk).
- **Collaboration**: Midwives work closely with OB/GYNs and anesthesiologists in hospitals. If an emergency arises (e.g., fetal distress, hemorrhage), they’ll **immediately escalate care** to a backup OB/GYN team.
- **Evidence**: A 2019 study in *PLOS Medicine* found that **out-of-hospital births attended by midwives have low rates of adverse outcomes** when complications are managed promptly. However, first-time moms are still advised to plan for transfer to a hospital if needed.
- **Your role**: Midwives encourage you to **trust your body and advocate for yourself**. If you feel something’s “off,” they’ll listen and act accordingly.
#### **OB/GYN Emergency Response**
- **Primary setting**: Hospitals, often in labor and delivery units with **24/7 backup teams** (anesthesiologists, neonatologists, surgeons).
- **Immediate access**: OB/GYNs can **order interventions faster** (e.g., C-sections, forceps, IV medications) if needed.
- **High-risk readiness**: Their training includes managing **placenta previa, preterm labor, or severe preeclampsia**, which may require intensive care.
- **Your role**: OB/GYNs will **explain risks and options clearly**, giving you time to process before making decisions.
*Representative story*: Emily, a first-time mom, chose an OB/GYN because of her history of gestational diabetes. *“I wanted someone who could monitor my blood sugar closely and be ready if my baby needed extra care. My provider assured me they’d handle anything, and I felt less anxious knowing that.”*
**Bottom line**: Both are prepared, but OB/GYNs may have slightly faster access to advanced interventions. If you’re low-risk and comfortable with natural birth, a midwife’s emergency plan—paired with a hospital backup—can be just as safe.
---
### **Can a Midwife Prescribe Medications for First-Time Moms During Pregnancy?**
Yes! Midwives are **licensed to prescribe medications**, including:
- **Common prenatal vitamins** (with folic acid, iron, etc.)
- **Meds for nausea** (like Diclectin or ginger supplements)
- **Pain relief** (e.g., acetaminophen for headaches)
- **Blood pressure medications** (if needed for preeclampsia)
- **Antibiotics** (for infections like UTIs or strep B)
*However, there are limits*. Midwives **cannot prescribe**:
- **Strong opioids** (like oxycodone)
- **Certain antibiotics** (e.g., fluoroquinolones)
- **Some hormonal treatments** (e.g., for thyroid disorders)
**What if I need something a midwife can’t prescribe?**
- They’ll **refer you to an OB/GYN** for specialty care.
- Many midwives have **collaborative practices** with OB/GYNs, so you can seamlessly transition if needed.
*Pro tip*: If you have a chronic condition (like asthma or epilepsy), discuss your medications with your provider **early in pregnancy**. Some drugs are safe, while others may need adjustments.
---
### **How Do Midwives vs. OB/GYNs Approach Cesarean Sections for First-Time Births?**
C-sections are **not inherently “better” with one provider over another**—but the *approach* can differ.
| **Factor** | **Midwife Care** | **OB/GYN Care** |
|--------------------------|------------------------------------------------------|------------------------------------------------------|
| **Vaginal birth support** | Strongly encourages natural labor; may use techniques like **hypnobirthing or water birth** to reduce C-section likelihood. | Offers evidence-based interventions (e.g., epidurals, pitocin) to manage labor progress. |
| **C-section rates** | Lower overall C-section rates for low-risk pregnancies (per ACOG). | Higher rates in high-risk cases, but also more prepared for emergency C-sections. |
| **Recovery focus** | Emphasizes **gentle recovery**, breastfeeding support, and emotional well-being. | Focuses on **medical recovery** (e.g., infection monitoring, pain management). |
| **VBAC support** | More likely to support **vaginal birth after C-section (VBAC)** if medically appropriate. | May offer VBAC but with stricter criteria (e.g., low transverse scar). |
*Did you know?* The **American College of Obstetricians and Gynecologists (ACOG)** now recommends **individualized care for C-sections**, meaning your provider should discuss risks, benefits, and alternatives—whether you’re planning a C-section or hoping to avoid one.
---
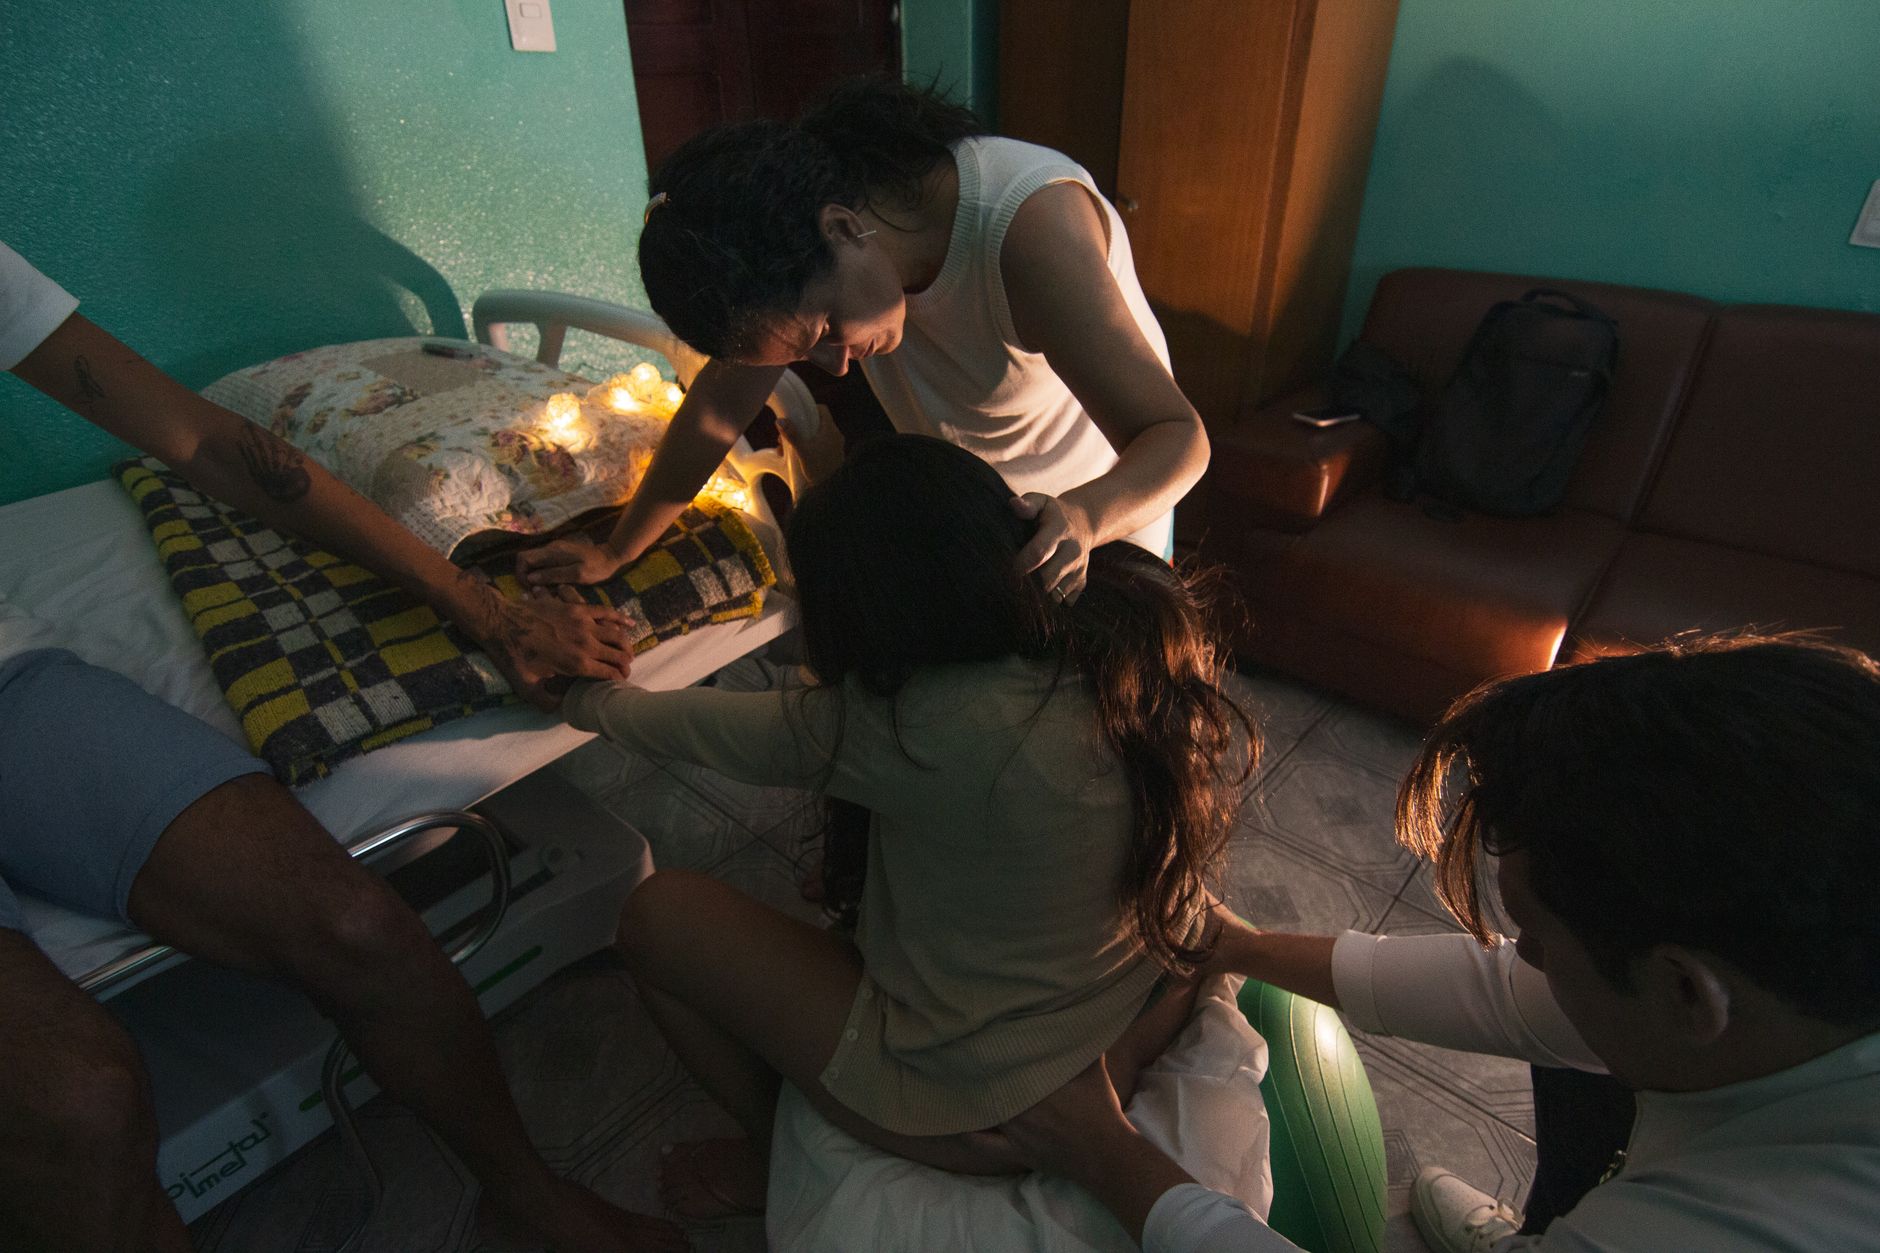 ---
### **What’s the Success Rate of VBAC (Vaginal Birth After C-Section) with a Midwife vs. OB/GYN?**
If you’ve had a previous C-section and want to try a vaginal birth, your provider’s approach matters.
#### **Midwife VBAC Support**
- **Success rate**: Studies show **VBAC success rates of 60–80%** when managed by midwives in hospitals with backup OB/GYN teams (*Journal of Midwifery & Women’s Health*, 2020).
- **Key factors for success**:
- **Low transverse scar** (most common type).
- **No uterine rupture risk factors** (e.g., previous uterine surgery).
- **Access to a hospital** with emergency C-section capability.
- **Midwives’ role**: They’ll monitor labor closely for signs of **uterine rupture** (e.g., sudden pain, fetal distress) and have a **clear transfer plan** to an OB/GYN if needed.
#### **OB/GYN VBAC Support**
- **Success rate**: Similar to midwives (**~60–80%**), but criteria may be stricter.
- **Hospital protocols**: Many hospitals have **VBAC bans** or require prior approval, which can limit options.
- **OB/GYN’s role**: They’ll assess your scar type and medical history, then create a **detailed birth plan** with backup protocols.
*Important note*: If you’re considering VBAC, **ask your provider about their hospital’s policies** before making a decision. Some facilities may not support VBAC at all.
---
 ---
### **How Do Midwives and OB/GYNs Differ in Handling Gestational Diabetes?**
Gestational diabetes (GDM) affects **6–9% of pregnancies** and requires careful management. Here’s how each provider typically approaches it:
#### **Midwife Approach**
- **Screening**: May use **oral glucose tolerance tests (OGTT)** or **glucose challenge tests (GCT)** as recommended by ACOG.
- **Management**:
- Focuses on **diet and lifestyle changes** (e.g., carb counting, meal timing).
- Encourages **physical activity** (walking, prenatal yoga).
- Offers **education on insulin management** if needed.
- **Collaboration**: If insulin is required, they’ll **refer you to an endocrinologist** or OB/GYN for oversight.
#### **OB/GYN Approach**
- **Screening**: Follows **ACOG guidelines** (usually between 24–28 weeks).
- **Management**:
- May **prescribe insulin or oral medications** (like metformin) if diet isn’t enough.
- More likely to **monitor blood sugar closely** with frequent testing.
- Works with **endocrinologists** for complex cases.
- **Delivery planning**: May recommend **earlier induction** (around 38–39 weeks) to reduce risks to the baby.
*Key difference*: Midwives lean on **natural management first**, while OB/GYNs may intervene earlier with medications. Both approaches are valid—**the right choice depends on your comfort level with monitoring and treatment.**
---
### **How Do Midwives vs. OB/GYNs Handle Placenta Previa in First Pregnancies?**
Placenta previa (when the placenta covers the cervix) occurs in **1 in 200 pregnancies** and requires specialized care.
#### **Midwife Management**
- **Initial diagnosis**: Midwives follow **ACOG guidelines** for ultrasound screening (usually at 18–22 weeks).
- **Restrictions**:
- Advise **pelvic rest** (no sex, no tampons).
- Recommend **limited activity** (no heavy lifting).
- Plan for **hospitalization if bleeding occurs**.
- **Delivery planning**: If previa is diagnosed early, they’ll **refer you to an OB/GYN** for delivery planning (usually **C-section at 36–37 weeks**).
#### **OB/GYN Management**
- **Diagnosis**: Confirm with **ultrasound and MRI if needed**.
- **Monitoring**:
- Schedule **frequent ultrasounds** to track placenta movement.
- May recommend **bed rest** if severe previa is suspected.
- **Delivery planning**:
- **C-section is standard** (vaginal birth is **not recommended** due to hemorrhage risk).
- Plan for **early delivery (36–37 weeks)** to reduce risks.
*Critical note*: Placenta previa is a **high-risk condition**, and **OB/GYN care is strongly recommended** for diagnosis and management. Midwives will **always refer you to an OB/GYN** if previa is suspected.
---
### **Do Insurance Plans Cover Midwife Care Equally to OB/GYN for First-Time Mothers?**
This is a **common concern**, and the answer depends on your plan. Here’s what to know:
- **Most major insurance plans** (Medicare, Medicaid, private insurers like Aetna, Blue Cross) **cover midwife care equally to OB/GYN care** for low-risk pregnancies.
- **Out-of-pocket costs**:
- **Midwife care**: May include **copays for visits, ultrasounds, and delivery**. Home births might require **additional out-of-pocket fees**.
- **OB/GYN care**: Typically **lower copays** for hospital deliveries, but **higher out-of-pocket costs** if you need specialist referrals.
- **Birth center vs. hospital**:
- **Birth centers** (midwife-led) may have **lower premiums** but higher deductibles.
- **Hospital births** (OB/GYN or midwife) are usually **fully covered** under most plans.
*Pro tip*: Check your **summary of benefits** online or call your insurer to confirm coverage. If you’re unsure, ask your provider’s office to verify.
---
 ---
### **Best Midwife vs. OB-GYN for First Pregnancy Based on Medical History**
Your **personal health history** should guide your choice. Here’s a quick guide:
| **Medical History Factor** | **Midwife May Be a Good Fit** | **OB/GYN May Be a Better Fit** |
|----------------------------------|------------------------------------------------------|----------------------------------------------------|
| **Low-risk pregnancy** | ✅ Yes, especially if you want natural birth support. | ✅ Yes, for peace of mind with medical backup. |
| **Gestational diabetes** | ⚠️ Possible, but may need OB/GYN referral for meds. | ✅ Best for close monitoring and insulin management. |
| **Hypertension or preeclampsia** | ❌ Not ideal; OB/GYN is safer. | ✅ Essential for blood pressure and medication. |
| **Previous C-section** | ✅ If VBAC is an option and hospital supports it. | ✅ For higher-risk VBAC or if hospital has restrictions. |
| **Placenta previa** | ❌ Referral to OB/GYN required. | ✅ Mandatory for diagnosis and delivery planning. |
| **Multiple gestation (twins)** | ⚠️ Possible, but higher monitoring needed. | ✅ Often recommended for closer fetal surveillance. |
| **Chronic conditions** (e.g., epilepsy, heart disease) | ⚠️ Possible with close collaboration. | ✅ Best for complex medical needs. |
*Remember*: **You can always switch providers** if your needs change. Many women start with a midwife and transition to an OB/GYN later in pregnancy if complications arise.
---
### **How Do Midwives and OB/GYNs Differ in Handling Induction for First-Time Pregnancies?**
Induction rates vary by provider, and the approach can differ significantly.
#### **Midwife Induction Approach**
- **When they recommend it**:
- **Medical reasons** (e.g., preeclampsia, postdates, fetal growth restrictions).
- **Patient preference** (e.g., if labor isn’t progressing naturally).
- **Methods they use**:
- **Non-pharmacologic**: Membrane sweeping, acupuncture, castor oil (though evidence is mixed).
- **Pharmacologic**: **Pitocin (oxytocin)** if needed, but often **avoid cervical ripening** (like Foley catheters) unless medically necessary.
- **Vaginal birth focus**: Midwives **strongly encourage trying labor** before considering C-section.
#### **OB/GYN Induction Approach**
- **When they recommend it**:
- **Medical reasons** (same as above) **plus** some elective inductions (e.g., convenience).
- **Hospital protocols** may push for induction earlier (e.g., at 39 weeks).
- **Methods they use**:
- **Cervical ripening**: Prostaglandins (like Cervidil) or Foley catheters.
- **Pitocin** for labor augmentation.
- **More likely to offer epidurals** to manage pain during induction.
- **C-section readiness**: OB/GYNs are **prepared for faster escalation** if labor doesn’t progress.
*Key difference*: Midwives **wait longer** for spontaneous labor, while OB/GYNs may induce earlier—especially if the baby is postdates or there are medical concerns.
---
 ---
### **What’s the Typical Communication Style: Midwife vs. OB/GYN for First-Time Mothers?**
This is where many women feel the biggest difference—and it can make or break your experience.
#### **Midwife Communication Style**
- **Holistic focus**: Discusses **emotional well-being, nutrition, and birth preferences** as much as medical concerns.
- **More time per visit**: Average visit length is **45–60 minutes**, allowing for **open-ended conversations**.
- **Patient-centered**: Encourages you to **ask questions and share concerns** without rushing.
- **Birth planning**: Spends time **creating a detailed birth plan** with you, including **coping strategies** (e.g., breathing techniques, positioning).
- **Postpartum support**: Offers **follow-up visits** for breastfeeding, emotional health, and recovery.
#### **OB/GYN Communication Style**
- **Medical focus**: Prioritizes **blood pressure, weight gain, and fetal monitoring** over lifestyle advice.
- **Shorter visits**: Average visit length is **20–30 minutes**, which can feel **rushed**.
- **Protocol-driven**: Follows **standardized care plans** (e.g., induction protocols, C-section guidelines).
- **Birth planning**: Provides **clear medical options** but may not have as much time for **personalized birth stories**.
- **Postpartum care**: May refer you to a **pediatrician and lactation consultant** for follow-up.
*Representative story*: Priya chose a midwife because she wanted someone who’d **listen to her fears about labor pain**. *“My OB/GYN visit felt like a checklist, but my midwife asked me about my fears and helped me practice breathing techniques. It made me feel so much more prepared.”*
**Bottom line**: If you value **deep emotional support and personalized care**, a midwife may be ideal. If you prefer **clear medical direction and quick access to interventions**, an OB/GYN might suit you better.
---
### **Myth vs. Fact: Midwife vs. OB/GYN Care**
Let’s debunk some common misconceptions:
#### **Myth: Midwives only do home births.**
**Fact**: While midwives **can** attend home births, **most first-time moms choose hospital or birth center deliveries** with midwives. Home births are **not for everyone** and carry slightly higher risks for first-time moms.
#### **Myth: OB/GYNs are always more “medical” and less “natural.”**
**Fact**: OB/GYNs **can** support natural birth! Many offer **unmedicated labor options, water birth, and minimal intervention**. The key is finding one who aligns with your goals.
#### **Myth: Midwife care is always cheaper.**
**Fact**: While midwife care can be **more affordable for low-risk pregnancies**, **hospital births (even with midwives) can be expensive**. Insurance coverage varies—always check your plan’s details.
#### **Myth: If I have a high-risk pregnancy, I must see an OB/GYN.**
**Fact**: Some **midwives specialize in high-risk care** and collaborate with OB/GYNs. However, **severe complications** (e.g., severe preeclampsia, twin pregnancy) often require OB/GYN oversight.
#### **Myth: Midwives don’t handle emergencies well.**
**Fact**: Midwives are **trained in emergency obstetric care** and work closely with OB/GYNs in hospitals. **Emergency C-sections and other interventions are managed safely** when midwives have backup support.
---
### **Key Takeaways: Midwife vs. OB/GYN for First Pregnancy**
Here’s a quick recap to help you decide:
1. **Midwife care is best if**:
- You want **personalized, holistic support**.
- You prefer **natural birth and minimal intervention**.
- You have a **low-risk pregnancy** and feel comfortable with home/birth center options.
- You value **longer visits and emotional well-being discussions**.
2. **OB/GYN care is best if**:
- You have a **high-risk pregnancy or chronic condition**.
- You want **quick access to medical interventions**.
- You prefer **shorter visits with clear medical protocols**.
- You’re concerned about **emergency preparedness**.
3. **Both are safe for low-risk pregnancies**, but **your comfort level and birth goals matter most**.
4. **You can always switch providers** if your needs change—many women start with a midwife and transition to an OB/GYN later.
5. **Ask questions early**: Talk to providers about their **induction policies, C-section rates, and postpartum support** to see if they align with your wishes.
6. **Trust your instincts**: If something doesn’t feel right, **find a provider who makes you feel heard and respected**.
---
### **Frequently Asked Questions About Midwife vs. OB/GYN for First Pregnancy**
#### **How do I know if my insurance covers midwife care?**
Most major insurance plans (including Medicare and Medicaid) **cover midwife care equally to OB/GYN care** for low-risk pregnancies. However, **birth center visits or home births may require additional out-of-pocket costs**. Check your **summary of benefits** or call your insurer to confirm. If you’re unsure, ask your provider’s office to verify coverage before committing.
#### **Can I choose a midwife if I’ve had a previous C-section?**
Yes! If you’re considering a **vaginal birth after C-section (VBAC)**, you can work with a midwife—**but only if your hospital supports VBAC**. Midwives are **encouraged to refer you to an OB/GYN for delivery** if VBAC isn’t an option. Always ask your provider about their **VBAC policies** before planning.
#### **Are midwives more likely to recommend induction for first-time pregnancies?**
Not necessarily. Midwives **tend to wait longer for spontaneous labor** before recommending induction. OB/GYNs may induce **slightly earlier** (especially if the baby is postdates or there are medical concerns). If you’re concerned about induction, ask your provider about their **labor management policies** during your first prenatal visit.
#### **How do midwives and OB/GYNs differ in handling postpartum care?**
Midwives often provide **more comprehensive postpartum support**, including:
- **Breastfeeding assistance** (lactation coaching, trouble-shooting).
- **Emotional well-being checks** (postpartum depression screening).
- **Physical recovery guidance** (perineal care, pelvic floor exercises).
OB/GYNs may refer you to a **pediatrician and lactation consultant**, but some also offer **postpartum visits** focused on recovery.
#### **What’s the best way to find a provider who aligns with my birth goals?**
1. **Ask for referrals**: Talk to friends, doulas, or local lactation consultants for recommendations.
2. **Check credentials**: Ensure your midwife is **certified by the American Midwifery Certification Board (AMCB)** and your OB/GYN is **board-certified by ACOG**.
3. **Attend a tour**: Visit the **birth center or hospital** where you’ll deliver to see the environment.
4. **Have a trial visit**: Meet with a provider for a **prenatal appointment** to see if you feel comfortable.
5. **Ask about policies**: Discuss **induction, C-section, and VBAC** plans upfront.
#### **Is it possible to have a midwife for prenatal care and an OB/GYN for delivery?**
Yes! Some women **start with a midwife for prenatal visits** and **transition to an OB/GYN for delivery**, especially if they’re concerned about high-risk scenarios. This is called **"shared care"** and is becoming more common. Just **communicate openly** with both providers to ensure seamless coordination.
---
### **When to See a Doctor or Specialist**
While both midwives and OB/GYNs provide excellent care for low-risk pregnancies, **you should seek immediate medical attention if you experience**:
- **Severe abdominal pain or cramping** (could indicate preterm labor or placental issues).
- **Vaginal bleeding** (especially bright red or heavy—this is **not normal** after the first trimester).
- **Sudden swelling, headaches, or vision changes** (possible signs of **preeclampsia**).
- **Decreased fetal movement** (contact your provider within 24 hours).
- **Fever over 100.4°F (38°C) with no other explanation**.
- **Leaking fluid** (could signal **premature rupture of membranes**).
If you’re unsure whether a symptom is serious, **err on the side of caution and call your provider**. Your safety—and your baby’s—is the top priority.
---
 ---
### **Final Thoughts: Trust Your Gut**
Choosing between a midwife and an OB/GYN for your first pregnancy isn’t about "better" or "worse"—it’s about **what feels right for you**. Some women thrive with a midwife’s **personalized, holistic approach**, while others feel reassured by an OB/GYN’s **medical readiness**.
*Remember*: **You’re not just choosing a provider—you’re choosing a partner for this journey.** Someone who will listen to your fears, celebrate your excitement, and stand by you no matter how your birth unfolds.
If you’re still unsure, **schedule a meeting with both**—ask about their **approach to labor, C-sections, and postpartum care**. Observe how they **communicate with you**. And trust yourself: **your instincts are your best guide.**
---
References
- American College of Obstetricians and Gynecologists (ACOG). (2021). *Midwifery Care*. https://www.acog.org
- World Health Organization (WHO). (2018). *Care in Normal Birth: A Practical Guide*. https://www.who.int
- Journal of Midwifery & Women’s Health. (2020). *VBAC Success Rates with Midwife-Led Care*. https://onlinelibrary.wiley.com
- PLOS Medicine. (2019). *Out-of-Hospital Birth Outcomes*. https://journals.plos.org
- American Midwifery Certification Board (AMCB). (2022). *Midwifery Standards*. https://www.midwife.org
- Mayo Clinic. (2021). *Choosing a Provider for Pregnancy*. https://www.mayoclinic.org

